
LESSON 13 · Body structure and function
Breathing: ventilation, gas exchange and regulation
Air entering the lungs, oxygen entering blood and blood delivering oxygen to cells are connected but distinct processes. Separating them clarifies what breathing rate, oxygen saturation and breathlessness can reveal.
What you will be able to do
- Explain how pressure changes drive ventilation.
- Distinguish ventilation, diffusion, perfusion and oxygen transport.
- Analyse information missing from respiratory measurements.
In this lesson
Why the lungs move with the chestNot every inhaled millilitre exchanges gasOxygen diffuses down a partial-pressure gradientOxygen saturation and total oxygen content are differentBreathing responds to metabolic and chemical signalsAnalyse the successive stages of respirationBilingual termsSourcesWhy the lungs move with the chest
Ventilation is bulk movement of air into and out of the lungs. During quiet inspiration, the diaphragm contracts and descends, enlarging the thoracic cavity. Mechanical coupling through the pleural system allows the lungs to expand, briefly lowering alveolar pressure below atmospheric pressure so air enters. Quiet expiration mainly uses elastic recoil. Forced breathing recruits additional muscles, so expiration is not always passive.
Lung tissue does not actively pull itself open like skeletal muscle. Pleural pressure reflects the interaction of lung recoil and chest-wall mechanics; disruption can impair their coupling. Increased airway resistance requires a larger pressure difference to sustain the same flow. Reduced lung distensibility requires more effort for the same volume change. Breathing difficulty can therefore involve airways, lung tissue, the chest wall or respiratory muscles. Visible chest movement alone cannot confirm that air is effectively reaching the gas-exchange regions.
Not every inhaled millilitre exchanges gas
The nose, trachea and larger bronchi conduct, warm and humidify air and contribute to defence. Air within these passages does not directly exchange across the alveolar membrane; this volume is anatomical dead space. Tidal volume is the amount moved in a breath. Minute ventilation multiplies tidal volume by frequency, whereas alveolar ventilation subtracts the portion that does not contribute effectively to exchange. Faster breathing need not improve that effective component.
Using invented teaching values, a tidal volume of 500 millilitres, rate of 12 and dead space of 150 millilitres gives approximately 4,200 millilitres of alveolar ventilation per minute. At 250 millilitres and 24 breaths, total ventilation stays 6,000, but model alveolar ventilation falls to 2,400. Actual dead space varies; this is not a formula for personal diagnosis. The comparison illustrates why shallow rapid breathing and deeper breathing can have different effects despite equal total air movement.
Measurements across the respiratory chain
| Measure | Main meaning |
|---|---|
| Respiratory rate | Breaths per minute |
| Tidal volume | Volume moved per breath |
| Saturation | Proportion of haemoglobin binding sites occupied by oxygen |
| Haemoglobin concentration | Transport protein per blood volume |
Major respiratory organs
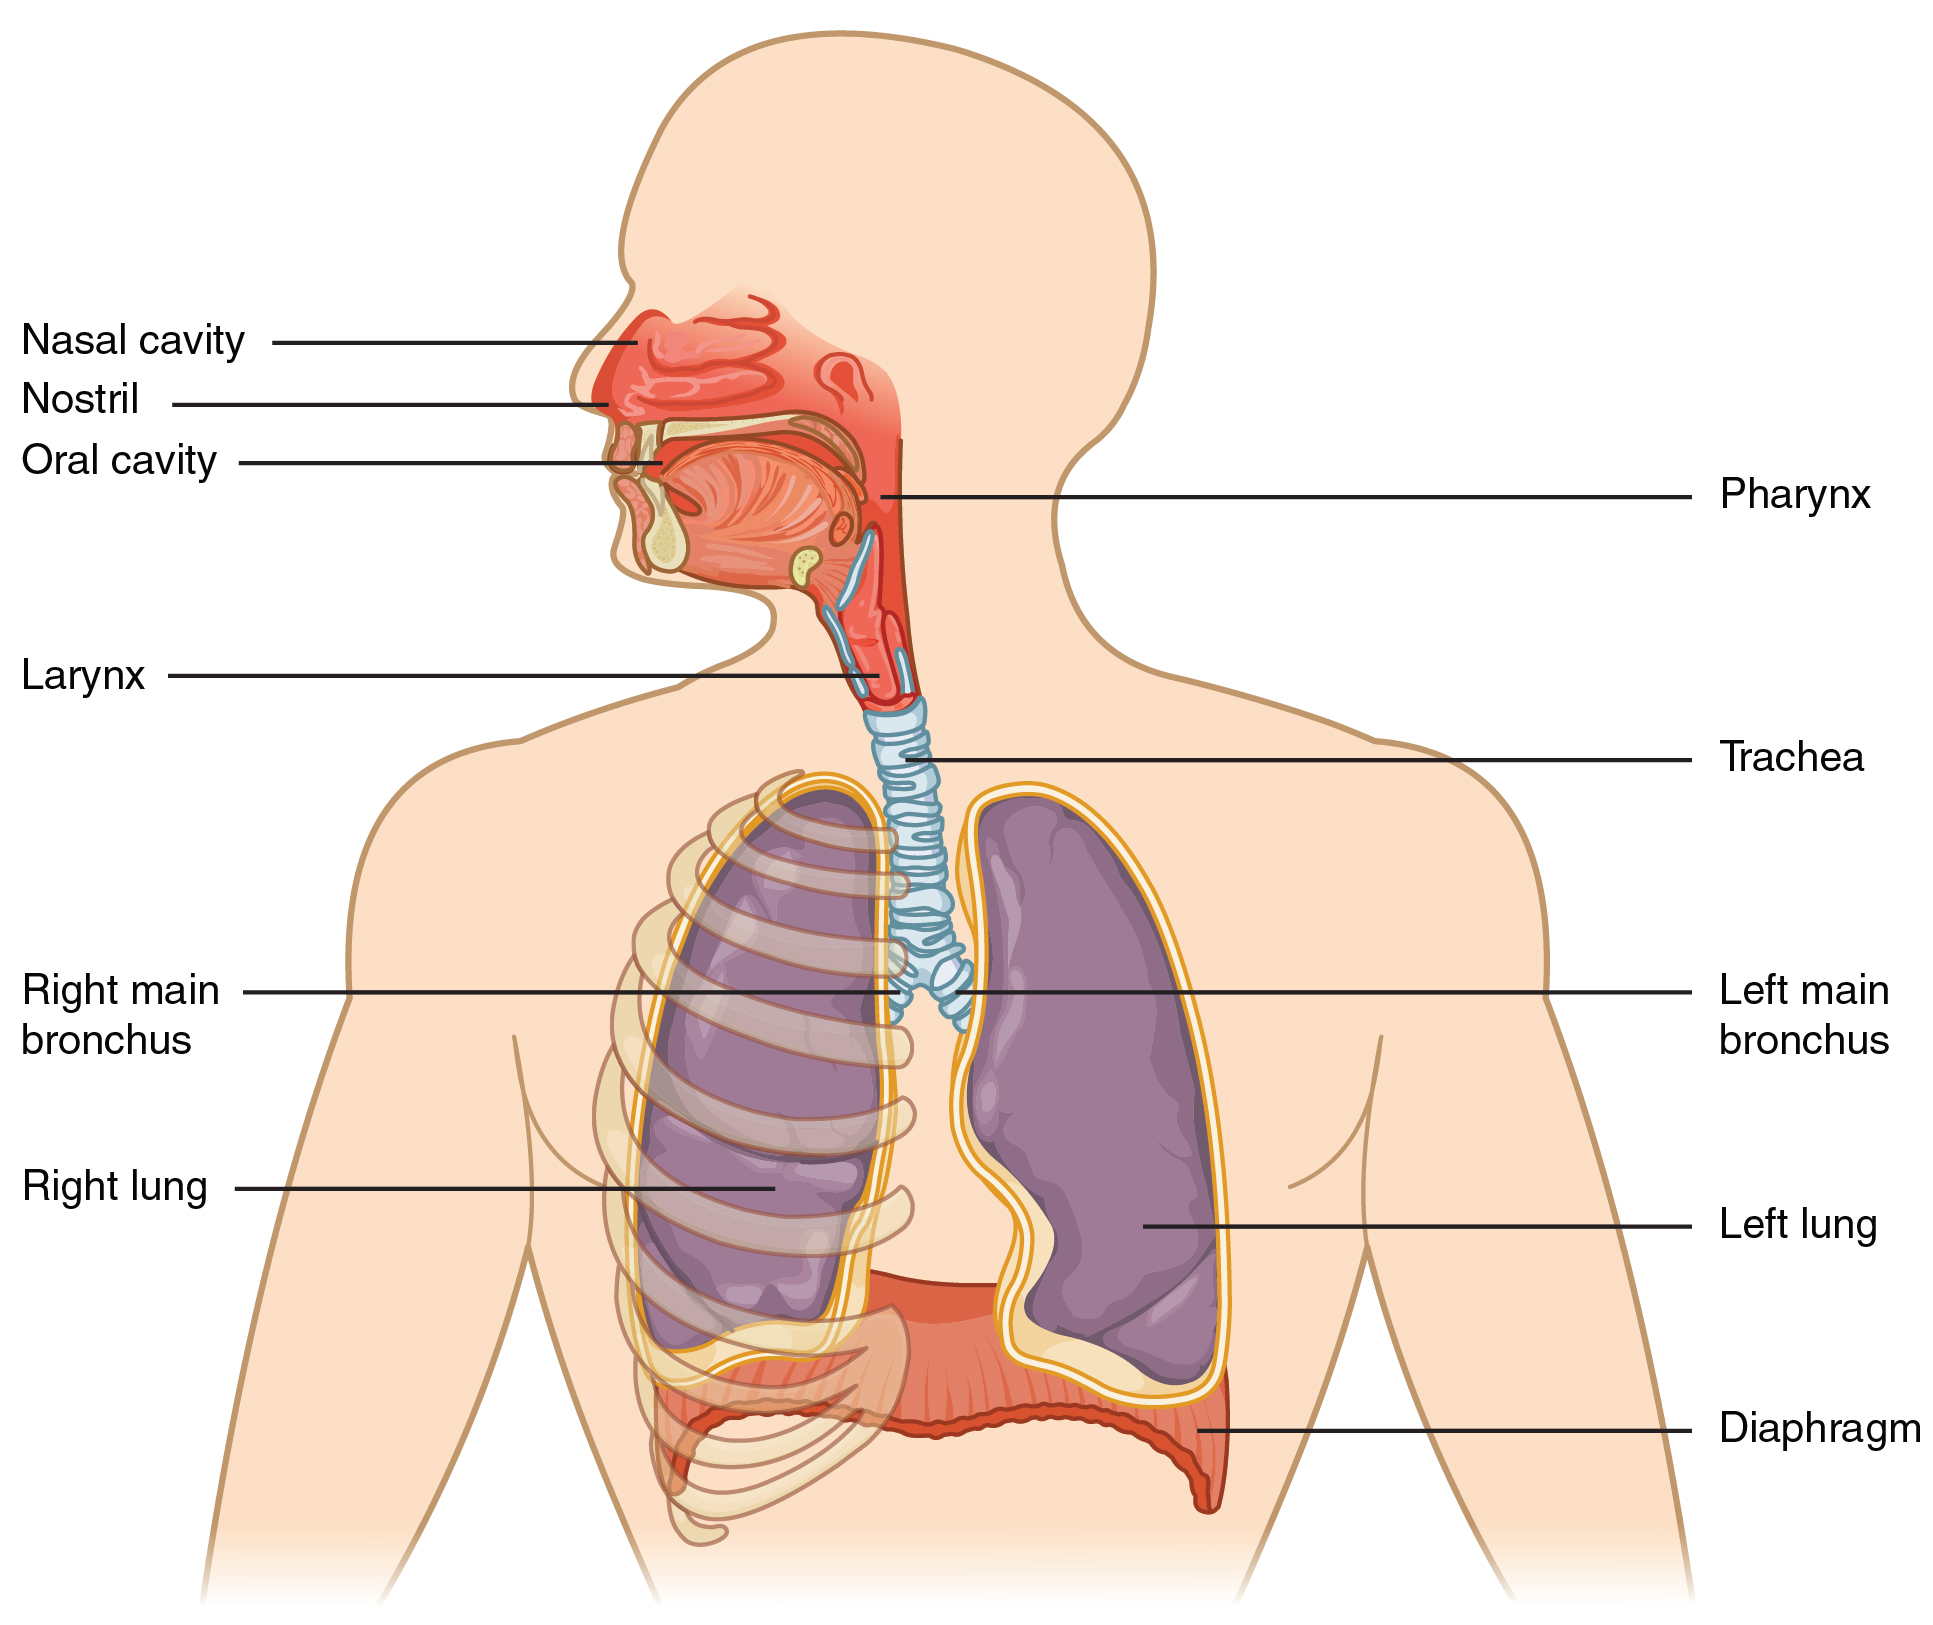
Major respiratory organs · OpenStax College · CC BY 3.0

| English label | Chinese equivalent |
|---|---|
| Nasal cavity | 鼻腔 |
| Pharynx | 咽 |
| Larynx | 喉 |
| Trachea | 气管 |
| Main bronchus | 主支气管 |
| Diaphragm | 膈肌 |
Alveoli and respiratory membrane
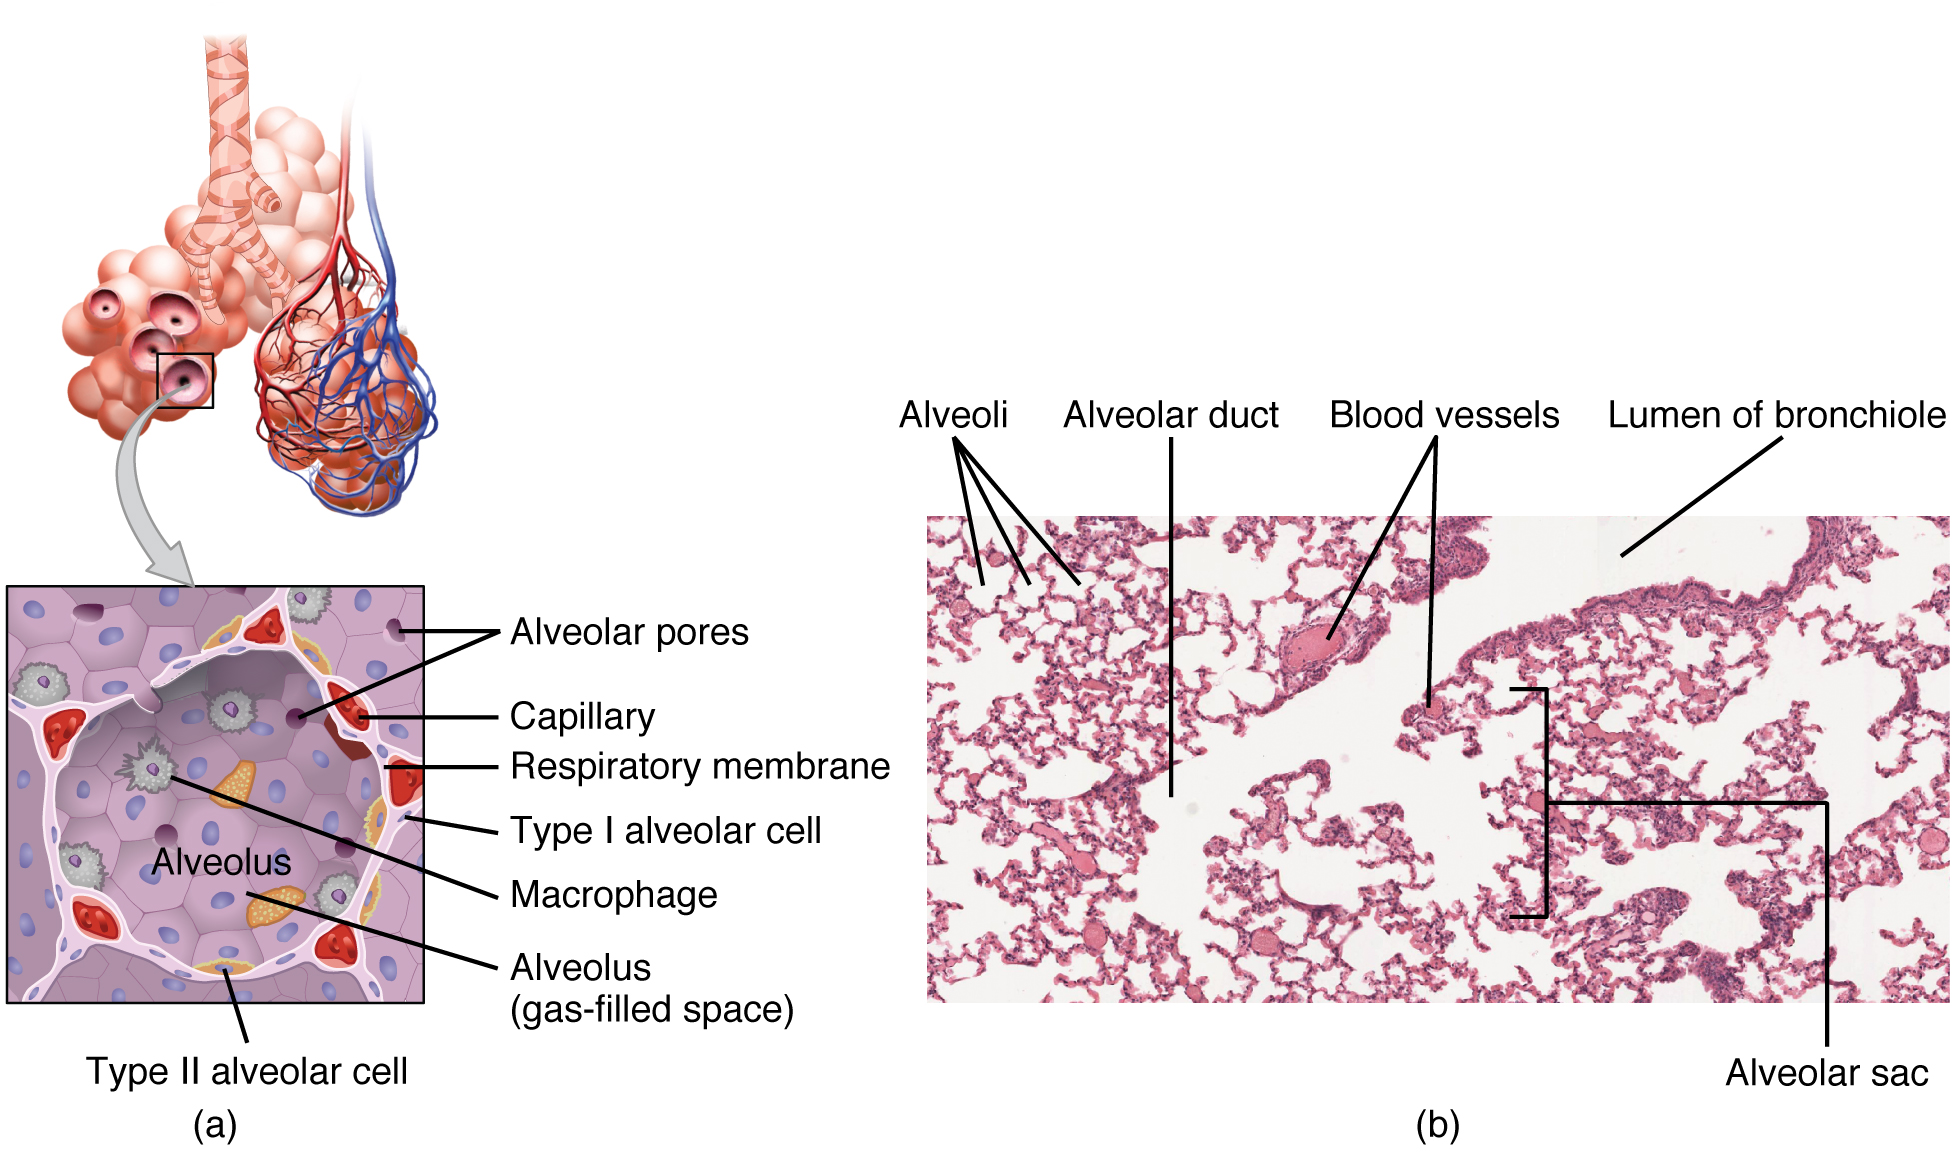
Alveoli and respiratory membrane · OpenStax College · CC BY 3.0

| English label | Chinese equivalent |
|---|---|
| Alveolus / Alveoli | 肺泡(单数/复数) |
| Capillary | 毛细血管 |
| Respiratory membrane | 呼吸膜 |
| Type I alveolar cell | Ⅰ型肺泡细胞 |
| Type II alveolar cell | Ⅱ型肺泡细胞 |
| Macrophage | 巨噬细胞 |
Diaphragm movement during breathing
Diaphragm movement during breathing · John Pierce · CC0 1.0

| English label | Chinese equivalent |
|---|---|
| Diaphragm | 膈肌 |
| Inspiration | 吸气 |
| Expiration | 呼气 |
Does faster breathing always increase alveolar ventilation?
Simplified model: alveolar ventilation = (tidal volume − dead-space volume) × respiratory rate. Compare 500 mL at 12 breaths/min with 250 mL at 24, holding dead space at 150 mL. Total ventilation is equal, but ventilation available for exchange differs. These are teaching assumptions, not breathing targets. Do not change your breathing to match them. The model cannot calculate blood oxygen or carbon dioxide.
Oxygen diffuses down a partial-pressure gradient
Alveolar air and capillary blood are separated by a thin respiratory membrane. Partial pressure is the contribution of one gas to the pressure of a mixture. Oxygen and carbon dioxide each diffuse down their own partial-pressure gradient. Less surface area, a thicker barrier or a smaller gradient can impair transfer. Surfactant lowers surface tension and helps stabilise alveoli; it is not an enzyme that actively pumps oxygen into blood.
Effective exchange also requires ventilation and perfusion to meet in the same regions. A ventilated alveolus with little blood flow contributes little oxygen to the body. Blood passing an inadequately ventilated region may leave poorly oxygenated. Whole-lung averages can conceal this unevenness. Imagine two exchange rooms, one supplied only with air and the other only with blood. Adequate totals would still fail to ensure effective transfer. Regional matching therefore matters alongside overall breathing and circulation.
Oxygen saturation and total oxygen content are different
Most oxygen entering blood binds to haemoglobin. Oxygen saturation describes the proportion of available binding sites occupied, not the total oxygen carried per litre. Reduced haemoglobin can therefore coexist with a high saturation and reduced carrying capacity. Arterial oxygen partial pressure relates to dissolved oxygen. It is physiologically connected to saturation and content but cannot simply substitute for either.
Carbon dioxide travels partly dissolved and partly attached to proteins, with a larger proportion transported after conversion into bicarbonate. This links respiratory transport with acid–base regulation. When tissues generate more carbon dioxide, circulation and ventilation must adjust together. The assumptions that more oxygen always relieves discomfort or that breathlessness always means low oxygen overlook breathing effort, carbon dioxide, circulation and central perception. A single finger-sensor reading cannot describe all these processes. Interpretation starts by naming what the instrument estimates and which clinically relevant variables it does not measure.
Breathing responds to metabolic and chemical signals
Brainstem networks generate and modify respiratory rhythm. Signals related to movement, emotion, the lungs and chemical conditions influence their output. Changes in carbon dioxide provide important feedback through their effects on acid–base conditions. Peripheral chemoreceptors also respond to arterial oxygen and other variables. Breathing drive cannot be reduced to “inhaling only when oxygen runs out,” and this physiology does not justify independently changing prescribed oxygen therapy.
At exercise onset, breathing can increase before major blood-gas changes occur, indicating contributions from central commands and feedback associated with muscle activity. Ventilation subsequently adjusts to carbon dioxide production. Hyperventilation means ventilation exceeds metabolic requirements for carbon dioxide removal, rather than simply a high breathing frequency. It may lower carbon dioxide and produce symptoms. This lesson uses scenarios and calculations rather than breath-holding, forced breathing or paper-bag experiments, because provoking symptoms adds no necessary evidence to understanding the feedback system.
Analyse the successive stages of respiration
For someone breathless after climbing stairs, separate four questions: can air move effectively, can alveolar gas exchange with blood, can blood carry and deliver sufficient oxygen, and has tissue demand increased? One symptom can arise through several mechanisms, and several stages may change together. Breathing rate describes rhythm; an oxygen estimate provides selected information about oxygenation. Neither independently evaluates carbon dioxide clearance or respiratory-muscle fatigue.
In a reasoning exercise, person A has reduced haemoglobin with preserved lung exchange, while person B has normal haemoglobin but poorly ventilated lung regions. Their potential oxygen-delivery problems occupy different stages, so a similar symptom does not establish the same response. Draw the sequence from air to membrane, haemoglobin, cardiac output and tissue. Place each observation at its appropriate stage. The central skill is distinguishing measurement, mechanism and inference, including recognising when the available evidence is insufficient.
Apply what you have learned
Why does equal minute ventilation not guarantee equal alveolar ventilation?
Read the explanation
The dead-space portion does not directly contribute to effective exchange. Different tidal-volume and rate combinations allocate different proportions to dead space; actual dead space and regional matching also matter.
Bilingual terms
- 通气 · Ventilation
- Bulk movement of air into and out of the lungs.
- 潮气量 · Tidal volume
- Air volume moved in a normal breath.
- 无效腔 · Dead space
- Ventilated space not effectively exchanging gas.
- 分压 · Partial pressure
- Pressure contributed by one gas in a mixture.
- 灌注 · Perfusion
- Blood flow through tissue or pulmonary capillaries.
Sources and further reading
- OpenStax: the process of breathing
- OpenStax: gas exchange
- OpenStax: transport of gases
- OpenStax: modifications in respiratory functions
Original course source-check record: 9 September 2026. Full Chinese and English sentence-by-sentence language review: 14 September 2026. AI editing and language review are not human clinical review. Linked institutions have not participated in or endorsed this course.
A moment in nature

Coral (Galaxea fascicularis), mar Rojo, Egipto, 2023-04-18, DD 128.jpg · Diego Delso · CC BY-SA 4.0
Converted to WebP; thumbnails may be cropped.
